

Stories
Staff Perspective: A Deeper Look at the Connections Between Stress, Trauma, and Suicide in Young Adults: New Research Findings
September 10, 2025
Suicide is a serious public health concern, especially for young adults who have experienced trauma. While a history of trauma can be a risk factor for suicide, we have a limited understanding of the specific mechanisms through which stress responses might contribute to this heightened risk. In a recent study, my colleagues and I investigated the links between suicidal thoughts and behaviors, and how individuals respond emotionally and physically to stress. Ninety-four undergraduate students (Mage=20.30; 61.7% women) were selected based on their lifetime exposure to at least one DSM-5 defined traumatic event.
The Study’s Approach
To see how participants reacted to stress, they completed two different breathing tasks in a controlled experimental lab setting:
- Voluntary Hyperventilation Challenge: This task involved breathing rapidly for three minutes. It’s designed to bring on physical sensations like fast heart rate or feeling lightheaded, which can sometimes trigger memories of traumatic events.
- Normal Breathing Control Task: This was a comparison task, similar in setup but with a regular calm breathing rate.
Throughout these tasks, we measured:
- Suicidal Thoughts and Behaviors: Participants completed the Suicide Behaviors Questionnaire-Revised at baseline, which asks about four key areas: suicidal thoughts or attempts over their lifetime, suicidal thoughts in the past year, threatening a suicide attempt, and how likely they felt to attempt suicide in the future.
- Self-Reported Psychological and Physiological Reactivity: Participants rated how they felt emotionally (e.g., helplessness, feeling unreal, urge to escape) and physically (e.g., tingling, shaking, chest pain, lightheadedness) using a part of the Panic Attack Questionnaire before and after each breathing task. We created a single "stress score" for each participant by subtracting their symptom change during the normal breathing task from their symptom change during the fast breathing task.
Key Findings
- Emotional Reactions Linked to Suicidal Ideation: Past-year suicidal ideation was significantly and positively associated with self-reported psychological reactivity to stress. This suggests that individuals reporting suicidal thoughts in the past year experienced a greater emotional distress during the stress-inducing task.
- No Clear Link to Physical Reactions: None of the four dimensions of suicidality, including past-year ideation, were associated with self-reported physiological reactivity to stress.
Conclusions
Our findings suggest that more recent suicidal ideation might be uniquely connected to a heightened emotional response to stress. This could be explained by how individuals with current suicidal thoughts interpret or “appraise” stressful events, perhaps seeing them as more threatening or overwhelming. Interestingly, we didn't see a link between suicidal thoughts or behaviors and self-reported physical reactions to stress. One possible explanation for this is a growing body of research on interoceptive deficits, which suggests that people at risk for suicide might have a reduced awareness of their body's internal signals. For example, their heart rate could rise during stress, but they might not consciously notice it as others would. This disconnect between mind and body could be even more pronounced in those who have previously attempted suicide. However, more research is needed, especially using physiological measures to more objectively assess an individual's stress response.
Clinical Takeaway
Understanding these specific patterns of reactivity can aid in developing more focused and effective support programs. This may include prioritizing the assessment of recent suicidal ideation and exploring how individuals interpret everyday stressors. These insights can directly inform treatment planning and guide the selection and development of interventions aimed at improving coping and reducing distress. It also highlights a growing interest in strategies that help people connect with and understand their bodily sensations, especially when they have a reduced awareness of these signals.
Limitations
It’s important to note that this study, like all research, has its limitations. The study's findings are based on self-reported physical reactions, and suicidal thoughts and behaviors were assessed at baseline rather than as a component of the experimental design. The study's population was also limited to trauma-exposed undergraduate students with recent alcohol use (part of a larger project). These characteristics are important to keep in mind when thinking about how broadly these findings apply to other populations.
The opinions in CDP Staff Perspective blogs are solely those of the author and do not necessarily reflect the opinion of the Uniformed Services University of the Health Science or the Department of Defense.
Linda Thompson, Ph.D., is a Postdoctoral Fellow with the Center for Deployment Psychology. Dr. Thompson earned her doctorate in Behavioral Science, Psychology from the University of North Texas and a master’s degree in Psychology from San Diego State University.
Study Reference
Thompson, L. M., Kearns, N. T., Rafiuddin, H. S., Contractor, A. A., & Blumenthal, H. (2025).
Associations of Suicidal Thoughts and Behaviors with Psychological and Physiological
Reactivity to a Hyperventilation Task Among Trauma-Exposed Emerging Adults.
Archives of Suicide Research, 1–16. https://doi.org/10.1080/13811118.2025.2524414
Additional References
Kearns, N. T., Blumenthal, H., Contractor, A. A., Guillot, C. R., & Rafiuddin, H. (2021). Effects of
bodily arousal on desire to drink alcohol among trauma-exposed college students.
Alcohol, 96, 15–25. https://doi.org/10.1016/j.alcohol.2021.07.002
Norton, G. R., Harrison, B., Hauch, J., & Rhodes, L. (1985). Characteristics of people with
infrequent panic attacks. Journal of Abnormal Psychology, 94(2), 216–221.
https://doi.org/10.1037//0021-843x.94.2.216
Osman, A., Bagge, C. L., Gutierrez, P. M., Konick, L. C., Kopper, B. A., & Barrios, F. X. (2001).
The Suicidal Behaviors Questionnaire-Revised (SBQ-R): Validation with clinical and
nonclinical samples. Assessment, 8(4), 443–454.
https://doi.org/10.1177/107319110100800409
Staff Perspective: When the Doctor Becomes the Patient - Recent Publications and a Selection of Resources for Moral Injury in Military Health Care Workers
September 3, 2025
 By
As noted by the VA’s National Center for PTSD, the majority of research into defining and understanding moral injury (MI) has been conducted with military service members and veterans, given that military-related experience tend to put people at greater risk for encountering potentially morally injurious events (PMIEs). Military PMIEs include many aspects of military service and combat, including killing or harming others, developing strategies or decisions that put others at risk, experiencing conflicting emotions when harming or killing others, and having to select or triage injured comrades with limited medical resources.
With the relatively high prevalence of MI in the general military having been established, a significant emphasis of research on MI in the military has been on identifying methods/tools for assessment and developing interventions for effective treatment. One critical aspect that is often overlooked though, is the consideration of situations where the doctor becomes the patient, or when health care providers experience MI themselves. This topic has become a bit better understood with the publication of two papers, one narrative review and one qualitative study, both examining MI in military medical personnel.
The first of these two publications is a review of MI across studies that included medical personnel and first responders from a diverse sampling of health care and emergency response professions (Rimon & Shetlef, 2025). The authors sought to better understand aspects of MI prevalence, risk, and outcomes within these populations. Although studies that focused exclusively on military populations were excluded, papers that included populations with military backgrounds, health care settings within military institutions, and outcomes relevant to military personnel were represented in the review and discussed by the authors. They noted that the reviewed studies identified unique challenges faced by military health care providers, including hierarchical decision making and dual obligations to mission and patients as contributing to elevated risk for MI in this group (Rimon & Shetlef, 2025). Several also discussed the frequent exposure of military clinicians to PMIEs in combat zones and operational environments. The authors note that military providers may experience conflict between their roles as a caregiver and as a service member, potentially forcing them to put mission over individual moral judgement and to follow orders that may conflict with professional and medical ethical standards. As a result, MI in military providers is frequently associated with symptoms such as sleep disturbances, anger, guilt, and long-term emotional distress (Rimon & Shetlef, 2025).
While the Rimon & Shetlef review takes a high-level approach to characterizing and understanding MI in military providers, a smaller qualitative study by Cole and colleagues (2025) examined MI on a much more personal level. A dozen military medical providers participated in semi-structured interviews about their experiences as military medical officers and their perceptions of moral injury. Through analysis of participant responses, the authors identified three primary themes regarding how military physicians experience moral injury (Cole, Shumaker, & Rudinsky, 2025). The first was an inability to provide standard of care that hindered their ability to fulfill the Hippocratic Oath. Within this theme, providers identified their position under their commander within the command hierarchy and a lack of resources in austere operational environments as contributing to an inability to provide adequate care. The second theme revolved around the ambiguity of caring for foreign nationals in both humanitarian and combat missions. When rendering humanitarian aid, some participants noted distress around leaving the situation without providing adequate follow-up care or feelings that the effort was primarily for show or diplomacy, not true impact. In combat situations, providers cited MI from conflicting thoughts and emotions around providing medical aid to enemy combatants and detainees. The final theme was personal impact, focused primarily on reconciling their own sense of morality with their military mission, resulting in cognitive dissonance, a loss of personal identity, and often MI (Cole, Shumaker, & Rudinsky, 2025). The authors go on to provider recommendations for better supporting and preparing military medical providers to cope when faced with these issues and dilemmas.
Fortunately, there are resources for health care providers, whether military or civilian, who are experiencing MI. While not military-specific, one helpful source for thinking about MI in medical providers is the Moral Injury in Health Care Workers website from the VA’s National Center for PTSD. Here you can find more information about potential sources and impacts of MI in health care workers, as well as self-care recommendations and support strategies for co-workers and leaders. The Consortium for Defense Psychology (CDP) also has links to recorded webinars on Adaptive Disclosure-Enhanced (AD-E) and Acceptance and Commitment Therapy for Moral Injury (ACT-MI), both strategies for addressing MI that can be used with affected health care workers.
The opinions in CDP Staff Perspective blogs are solely those of the author and do not necessarily reflect the opinion of the Uniformed Services University of the Health Science or the Department of Defense.
Jenny Phillips, Ph.D., is the Associate Director of Program Evaluation for the Center for Deployment Psychology (CDP) at the Uniformed Services University of the Health Sciences in Bethesda, MD.
References:
Cole, R., Shumaker, J. T., & Rudinsky, S. L. (2025). “It’s there and you’re changed forever”: military
physicians’ perceptions of moral injury. Journal of Military Ethics, 1-13.
Rimon, A., & Shelef, L. (2025). Moral Injury Among Medical Personnel and First Responders Across
Different Healthcare and Emergency Response Settings: A Narrative Review. International Journal of
Environmental Research and Public Health, 22(7), 1055.
Staff Perspective: Moral Distress and Moral Injury - How Prevalent Are They in U.S. Veterans?
August 27, 2025
 Moral injury remains a murky concept, despite the growing body of literature on this important topic. While there’s not a consensus on exactly what moral injury is, Phelps et al. (2024) describe it as enduring psychological, social, and spiritual distress that can occur when individuals are exposed to high-pressure situations that violate or clash with their deeply-held moral beliefs or values. Moral injury may stem from one’s own actions or inactions, the actions of others, or a perceived betrayal by trusted leaders or institutions. In military contexts, including those with complex rules of engagement, moral injury may occur after engaging in or witnessing acts that conflict with one’s sense of right and wrong, such as causing harm to civilians, being unable to prevent the loss of life, seeing human suffering, or feeling deeply misled by command.
Litz et al. (2022) nicely differentiate moral injury from moral distress, noting that moral injury requires exposure to potentially morally injurious events (PMIEs) that involve both agentic acts (committing or failing to prevent transgressions oneself) and non-agentic experiences (witnessing or being directly affected by others' transgressions). In contrast, moral stress involves exposure to moral stressors that are less severe or lower-magnitude transgressive experiences. Moral distress is a preclinical condition with less functional impairment than moral injury.
Refinements in the definition of moral injury like those mentioned above, as well as the development of psychometrically-validated measures, are helping us better understand this concept. The Moral Injury Outcomes Scale (MIOS; Litz et al., 2022) has individuals consider whether they have been exposed to different types of PMIEs, and if they have, they proceed to respond to 14 items based on two subscales: shame and trust violation. Afterwards, they indicate the impact of moral injury symptoms on different aspects of their life by responding to an eight-item functional outcome measure adapted from the Brief Inventory of Psychosocial Functioning. Learn more about the MIOS here: https://sites.bu.edu/litzlab/additional-resources-on-moral-injury/.
Last year, I wrote about another useful self-report measure called the Moral Injury and Distress Scale (MIDS; Norman, Griffin, Pietrzak, McLean, Hamblen, & Maguen, 2024). Discover more about it here: https://ptsd.va.gov/professional/assessment/te-measures/mids.asp.
Between 2-10 November 2023, Litz et al. used the MIOS to survey a nationally representative sample of 3,002 U.S. veterans online about exposure to PMIEs and identify rates of moral distress and moral injury. The results are hot off the press (Litz et al., 2025). The goal was to estimate the prevalence and significance of these conditions to help educate clinicians and inform future directions in the field. The authors stress that “understanding the prevalence and characteristics of moral distress and moral injury is essential for tailoring prevention efforts, supporting affected individuals, and informing clinical and policy decisions.” Based on the survey results, 44.7% of the respondents endorsed PMIEs. What do you think about this rate? Are you surprised? More specifically:
- 45.2% reported non-agentic experiences in which they witnessed others’ transgressions
- 40.2% reported non-agentic experiences in which they were directly affected by others’ transgressions
- 14% reported agentic experiences in which they committed or failed to prevent transgressions
Interestingly, exposure to PMIEs was more likely among veterans who were female, younger, lower-income, unmarried, and had some college education. PMIE exposure was also more likely to be reported by veterans who had deployed to a warzone or held junior enlisted ranks. According to the authors, these findings suggest that exposure to PMIEs is not an inevitable part of military service. In other words, we shouldn’t make the assumption that all service members experience PMIEs. Why veterans with these backgrounds were more apt to experience PMIEs is unclear. Also, I’m curious if those who completed the survey may have underreported PMIEs, particularly PMIEs involving acts of perpetration.
With respect to rates of moral distress and moral injury in the full sample, these were relatively low. The prevalence was 4.1% for moral distress and 5.9% for moral injury. Keep in mind that lower overall rates were expected, since veterans who did not endorse PMIEs were included in the rates but were not at risk for these conditions. However, even among those who reported experiencing PMIEs, the rates were not very high—9.1% for moral distress and 13.1% for moral injury. The authors suggest that these relatively low rates underscore that, like PTSD, moral distress and moral injury are tied to specific stressful events and that PMIE exposure, in and of itself, does not automatically lead to moral distress or moral injury. At the same time, for those who suffer from moral distress or moral injury, providing access to psychoeducation, support, and treatment is critical. Additionally, it’s essential when working with clients that we try to prevent moral distress from morphing into moral injury—a much more debilitating and enduring condition.
Certain factors were associated with a greater likelihood of moral injury, including Hispanic ethnicity, not being married, older age, and endorsing agentic PMIEs (events involving committing or failing to prevent transgressions). Moral distress was more likely among those veterans who were female, older, had deployed to warzones (especially multiple times), and those who had experienced agentic PMIEs. Based on these findings, the authors propose that moral distress and moral injury are shaped by a person’s characteristics and social support, as well as occupational, structural, and broader institutional factors that influence how they process and recover from transgressive experiences. I’m glad to see research results like this on prevalence rates in veterans, yet the findings reveal we have much more to uncover.
Additional Resources
For more information about moral injury, visit the National Center for PTSD: https://www.ptsd.va.gov/understand/related/moral_injury_ptsd.asp
For a practical book on moral injury, with chapters dedicated to different clinical approaches for helping clients with moral injury, check out Addressing Moral Injury in Clinical Practice: https://www.apa.org/pubs/books/addressing-moral-injury-clinical-practice
The opinions in CDP Staff Perspective blogs are solely those of the author and do not necessarily reflect the opinion of the Uniformed Services University of the Health Science or the Department of Defense.
Paula Domenici, Ph.D., is the Director, Civilian Public & Private Partnerships (CP3) at the Center for Deployment Psychology (CDP) at the Uniformed Services University of the Health Sciences in Bethesda, Maryland. She oversees the development of courses and training programs for providers on evidence-based treatments for service members and veterans.
References
Litz, B. T., Plouffe, R. A., Nazarov, A., Murphy, D., Phelps, A., Coady, A., Houle, S. A., Dell, L.,
Frankfurt, S., Zerach, G., & Levi-Bels, Y., and the Moral Injury Outcome Scale Consortium.
(2022). Defining and assessing the syndrome of moral injury: Initial
findings of the moral injury outcome scale consortium. Frontiers in Psychiatry,
13, 923928. https://doi.org/10.3389/fpsyt.2022.923928
Litz, B. T., Walker, H. E., Pietrzak, R. H., Rusowicz-Orazem, L. (2025), The prevalence of moral
distress and moral injury among U.S. veterans, Journal of Psychiatric Research, 189,
435-444. https://doi.org/10.1016/j.jpsychires.2025.06.031
Norman, S. B., Griffin, B. J., Pietrzak, R. H., McLean, C., Hamblen, J. L., & Maguen, S. (2024).
The moral injury and distress scale: Psychometric evaluation and initial validation in
three high-risk populations. Trauma Psychology: Theory, Research, Practice, and Policy,
16(2), 280-291. https://doi.org/10.1037/tra0001533
Phelps, A., Adler, A. B., Belanger, S. A., Bennet, C., Cramm, H., Dell, L., Fikretoglu, D., Forbes,
D., Heber, A., Hosseiny, F., Morganstein, J. C., Murphy, D., Nazarov, A., Pedlar, D.,
Richardson, J. D., Sadler, N., Williamson, V., Greenberg, N., & Jetly, R. (2024).
Addressing moral injury in the military. BMJ Military Health, 170(1),
51-55. http://dx.doi.org/10.1136/bmjmilitary-2022-002128
Staff Perspective: The Lingering Why
August 20, 2025
 By
Any parent would tell you the “why” questions start when we are young, usually around two- or three-years-old. The constant need to know the reason behind function, choices, and existence is inherent in us. We want to understand, and maybe if we can understand something, we feel more comfortable with it. The question of “why” helps us understand our surroundings, and this curiosity keeps us learning and growing. As we get older our “whys” tend to become more existential or morality based. Questions like why do people act the way they do, or why do I struggle with right and wrong? These create an opportunity for personal growth and introspection. But what about when we cannot explain things? What if there is no ability to answer, “why”? The loss of a loved one to suicide can create this eternal, uncertain “why”.
When we can answer a “why” question we feel more in control, perhaps more certain. But there are many situations in life where we cannot find these answers. Why do bad things happen to good people? Why do we experience suffering? Why do we exist? The lack of certainty or answers for these questions can cause significant emotional distress or internal turmoil. When thinking about suicide, we are faced with many unanswered “whys”. Why didn’t they tell me how they felt? Why didn’t they ask for help? Why was there no other option? For surviving family members, these “whys” can complicate, elongate the grief process, and even impact their ability to return to some resemblance of normal. How do we as clinicians, or even as friends or family help people navigate this vexing cycle of the unknown?
As a provider, when someone comes for help after the loss of a loved one to suicide, we may assume a normal grief and loss process. We can work through Kubler- Ross’s stages, we can tell them there is no right timeline for grieving, we can process emotions, but what we cannot do is answer their question of “why.” Because we really do not know why people die by suicide. We have theories of suicide, we know risk factors, we can identify warning signs, but this is one of life’s “why” questions that we cannot answer with firm scientific data. The reality is, even with insight into stressors and symptoms, even if a note is left, we never know what that final thought was. We need to be able to support our clients in their struggle to understand why, and also assist them with accepting the lack of resolution.
So how can we start this process of addressing the lingering why questions? At the core of all therapy is positive unconditional regard. Suicide can carry a stigma that other losses, like terminal illness or accidental death, do not. Family and friends may even question if it is acceptable for them to openly grieve. Normalizing this concern, and providing the supportive environment to grieve is a key component for processing. Addressing the existential piece can be more complex and difficult to navigate. Sometimes the unknown can help provide comfort, if reframed in a useful way. While we do not have a definite answer for why, this allows us to create our own narrative that brings peace. We get to decide how we understand the circumstances and accept them. For example a family member may be able to emotionally accept a death by suicide when put in context with physical suffering, loss of job, or other extreme stressors, even if these factors were only a piece of the situation. When we choose to write the narrative of understanding, we get to assign the meaning. We accept the view that helps us cope and brings understanding.
With acceptance of the unknown, or creating a narrative that helps with coping, we can focus on addressing the other complexities that arise after a loss from suicide. A suicide can cause post-traumatic stress disorder symptoms, and trauma focused treatment may help with processing. Families may benefit from systems therapy, particularly as the system has been altered. Cognitive therapy can be utilized to address unhelpful thought patterns and work to increase resocialization. When someone is able to reach a point of acceptance, they can move into more targeted therapies.
Working with our patients, we can focus on finding the narrative that brings enough resolution that they can start to think about the future, and what forward movement looks like for them. These lingering questions of “why” may continue to arise, but with support, understanding, and a narrative that brings solace, surviving family members may start to see a path forward.
The opinions in CDP Staff Perspective blogs are solely those of the author and do not necessarily reflect the opinion of the Uniformed Services University of the Health Science or the Department of Defense.
Kristyn Heins, Ph.D., is a Licensed Professional Counselor serving as a Military Behavioral Health Counselor for the Center for Deployment Psychology (CDP) at the Uniformed Services University of the Health Sciences in Bethesda, Maryland. In this role, she supports the CDP’s efforts of training clinicians in evidenced-based practice focused on suicide prevention.
Staff Perspective: Sleep is for the Strong - Empowering Service Members Through Shared Decision Making
August 13, 2025
 By Jaime Rodden
Sleep isn’t just a personal health issue for service members; it’s a mission-critical factor that affects unit cohesion, operational performance, and overall force readiness. Yet for years, military culture sent a different message. Pushing through exhaustion was worn like a badge of honor, and phrases like “I’ll sleep when I’m dead” were all too common. Sleep deprivation was seen as a sign of toughness rather than a threat to mission success. Thankfully, the conversation is shifting.
As research in this area grows, it’s undeniable how deeply sleep impacts the three essential domains of service member performance: physical, cognitive, and social functioning. As such, sleep is finally being recognized as a critical component of readiness. Still, there's more work to do. Leadership and service members need stronger buy-in, and healthcare providers need practical tools to support military-connected patients facing sleep challenges.
The shared decision making model may be the missing link. Shared decision making is an evidence-based approach that helps patients feel more involved in their care by making sure they fully understand their treatment options. Instead of being told what to do, they’re invited into a conversation, one where their concerns, preferences, and goals are part of the plan. This collaborative approach between provider and patient builds trust, encourages engagement, and gives individuals more control over their path to better sleep.
Bringing shared decision making into sleep health conversations is starting to gain momentum in military settings. The Department of Defense’s clinical practice guidelines recommend it as a key strategy to help service members and providers make joint decisions about sleep treatment options. And there’s solid research behind it. Shared decision making has been shown to boost self-management and increase motivation, both of which are essential when tackling challenges like sleep deprivation and disorders like insomnia.
One easy way to bring shared decision making into sleep health education is infographics. They’re visually engaging, easy to digest, and just as effective as traditional text when it comes to retaining information. With that in mind, our team designed a series of infographics tailored for healthcare providers and military leadership. These visuals are meant to support shared decision making conversations by clearly illustrating how sleep deprivation affects readiness, using a biopsychosocial lens to connect sleep to physical, cognitive, and social performance across the Force.
Interested in using the infographics with a military-connected patient? Check them out here: https://deploymentpsych.org/content/sleep-health-handouts
See Also - Staff Perspective: Sleep Isn’t Optional, It’s Operational
The opinions in CDP Staff Perspective blogs are solely those of the author and do not necessarily reflect the opinion of the Uniformed Services University of the Health Science or the Department of Defense.
Jaime Rodden is a Clinical Research Manager for the Center for Deployment Psychology (CDP). She received her Bachelor of Science in Exercise Science from Linfield University, and Master of Science in Exercise Physiology from California State University, Fullerton.
References
Kinney, A. R., Brenner, L. A., Nance, M., Mignogna, J., Cobb, A. D., Forster, J. E., ... & Bahraini, N. H. (2024). Factors influencing shared decision-making for insomnia and obstructive sleep apnea treatment among veterans with mild traumatic brain injury. Journal of Clinical Sleep Medicine, 20(5), 801-812.
Legare F, Witteman HO. Shared decision making: examining key elements and barriers to adoption into routine clinical practice. Health Aff (Millwood). 2013;32(2): 276–284.
Staff Perspective: Sleep Isn’t Optional, It’s Operational
August 6, 2025
 By Jaime Rodden
Most of us have struggled with getting enough sleep at some point, but when you compare sleep habits between civilians and service members, the difference is striking. While about a third of the general population reports not getting the recommended seven hours of sleep per night, the number jumps to more than 85% among service members.
So why is sleep such a major challenge for military personnel? A 2024 report from the Government Accountability Office (GAO) provides some answers. Medical conditions, like insomnia, sleep apnea, PTSD, depression and anxiety, substance abuse, and TBI are all common and all negatively affect sleep. On top of that, challenging work hours are also a frequently reported problem. Service members often work irregular shifts, pull long hours, and wake up early, sometimes in high-stress, high-stakes environments. For deployed service members, sleeping gets even tougher due to poor conditions like loud noise, bad lighting, uncomfortable bedding, and extreme temperatures. All of these factors play a role in the reduced sleep health of service members. Sleep doesn’t just impact service members’ health, it impacts force readiness.
Force readiness is the “ability of military forces to fight and meet the demands of assigned missions in line with national strategy”. A key piece of this sentiment is combat readiness, which depends heavily on personnel being at the top of their game physically, cognitively, and socially. These three connected areas, known as the biopsychosocial model, can be severely impacted by sleep deprivation.
Physical Readiness
Sleep plays a major role in physical performance. It affects strength, endurance, visual sharpness, and the ability to carry out complex military tasks like handling firearms or executing tactical maneuvers. When service members are sleep deprived, they don’t just feel tired, they lift less, run slower, and their responses are delayed. They’re also more prone to injuries and weight gain, which can lead to early separation from service and higher healthcare costs. The physical impact goes far beyond what the average individual may experience after a night of poor sleep, it affects mission outcomes and force readiness.
Cognitive Readiness
Cognition is another critical piece. Reaction time, memory, focus, decision-making, and reasoning all take a hit when someone is sleep-deprived. In a military setting, even small mistakes can lead to severe consequences. Sleep also affects emotional regulation, making it harder to manage frustration or confusion and easier to fall into negative mood states. Mental fatigue makes even routine tasks feel more physically demanding, increasing the risk of injury, burnout, or mistakes.
Social Readiness
Sleep impacts how we relate to and work with others. This includes communication, teamwork, empathy, impulse control, and emotional intelligence. These abilities are crucial to effective teamwork and unit cohesion, which play a large role in mission success. Sleep deprived service members may find it harder to connect with others, resolve conflicts, or collaborate effectively. For leaders, the impact can be even more serious. Sleep-deprived leaders tend to struggle with decision-making, critical thinking, and memory, which can affect the entire unit. Interestingly, studies show that effective leadership can actually counteract some of the negative effects of sleep deprivation on team performance, making sleep a leadership issue too.
The Bottom Line
Sleep is more than just a health concern. It’s a readiness issue that affects every level of military performance, from the individual service member to the entire force. As research continues to unpack the full scope of how sleep shapes physical, cognitive, and social functioning, one thing is clear: sleep isn’t optional, it’s operational.
With this in mind, our team developed a series of targeted infographics designed to highlight how sleep is essential for operational readiness. These resources are tailored to meet the unique needs of different military audiences, including branches like Space Force, and leadership roles. Our goal is to equip service members with practical, actionable information to encourage them to prioritize sleep, and in turn, improve their performance and enhance combat readiness. The infographics can be accessed here: https://deploymentpsych.org/content/sleep-health-handouts
The opinions in CDP Staff Perspective blogs are solely those of the author and do not necessarily reflect the opinion of the Uniformed Services University of the Health Science or the Department of Defense.
Jaime Rodden, is a Research Coordinator for the Center for Deployment Psychology (CDP). She received her Bachelor of Science in Exercise Science from Linfield University, and Master of Science in Exercise Physiology from California State University, Fullerton.
References:
JCS, J. P. (2017). Doctrine for the Armed Forces of the United States, DOD,
Incorporating Change 1, July 12, 2017. GL-10.
https://www.jcs.mil/Portals/36/Documents/Doctrine/pubs/jp1_ch1.pdf?ver=2019-02-11-174350967
Office, G. A. (2024). Military readiness: Comprehensive approach needed to address
service member fatigue and manage related efforts.
https://www.gao.gov/assets/gao-24-105917.pdf
Mysliwiec, V., Gill, J., Lee, H., Baxter, T., Pierce, R., Barr, T. L., Krakow, B., & Roth, B. J.
(2013). Sleep disorders in US military personnel: a high rate of comorbid insomnia and
obstructive sleep apnea. Chest, 144(2), 549-557.
Grandou, C., Wallace, L., Fullagar, H. H., Duffield, R., & Burley, S. (2019). The effects of
sleep loss on military physical performance. Sports Medicine, 49(8), 1159-1172.
Engel, G. L. (1977). The need for a new medical model: a challenge for biomedicine.
Science, 196(4286), 129-136.
LaGoy, A. D., Conkright, W. R., Proessl, F., Sinnott, A. M., Beckner, M. E., Jabloner, L.,
Eagle, S. R., Sekel, N. M., Roma, P. G., & Dretsch, M. N. (2023). Less daytime
sleepiness and slow wave activity during sleep predict better physical readiness in
military personnel. Sleep Health, 9(1), 93-99.
LoPresti, M. L., Anderson, J. A., Saboe, K. N., McGurk, D. L., Balkin, T. J., & Sipos, M. L.
(2016). The impact of insufficient sleep on combat mission performance. Military
Behavioral Health, 4(4), 356-363.
Killgore, W. D. (2010). Effects of sleep deprivation on cognition. Progress in brain
research, 185, 105-129.
Killgore, W. D., Kahn-Greene, E. T., Lipizzi, E. L., Newman, R. A., Kamimori, G. H., &
Balkin, T. J. (2008). Sleep deprivation reduces perceived emotional intelligence and
constructive thinking skills. Sleep medicine, 9(5), 517-526.
Olsen, O. K., Pallesen, S., Torsheim, T., & Espevik, R. (2016). The effect of sleep
deprivation on leadership behaviour in military officers: An experimental study. Journal of
sleep research, 25(6), 683-689.
Staff Perspective: Through SPC Jones’ Eyes - How Stigma Disrupts Mental Health Support for Service Members
July 30, 2025
 By
Mental health stigma remains one of the most persistent barriers to care for service members. It operates at multiple levels—internally, socially, and institutionally—limiting help-seeking behavior and impacting readiness and relationships.
This four-part fictional vignette follows a day in the life of a junior enlisted soldier. After each act, we explore how different forms of stigma shape the individual’s behavior, relationships, and access to care.
As you read, consider: How might you recognize and respond to stigma in your work with service members?
Act I: The Couch
Specialist Sean Jones sits up abruptly, gasping for air. He realizes he's not at the field exercise—he’s just awakened from a vivid nightmare, drenched in sweat. A junior enlisted soldier recently returned from training, Sean witnessed a serious accident during the exercise that resulted in the likely medical discharge of a close friend. His wife, Stacey, groggily rolls over and asks if he’s okay.
“I’m fine,” he snaps, grabbing his pillow and heading to the couch.
Alone and restless, he tosses and turns, ruminating about the upcoming training. He worries that his nightmares, jumpiness, and unexpected urges to cry are signs of weakness. He fears this “weakness” will result in his failing the next training exercise. In reality, he feels like he doesn't deserve to be in the Army. And that makes him feel guilty because he’s still in and his friend’s career is over. After tossing and turning for hours, Sean gets up the next morning, tired and irritable, and leaves for work without speaking to Stacey. He wants to apologize but that means he’ll have to talk about what was going on with him and he “just can’t do it.” So instead he starts his day feeling exhausted, ashamed, and alone.
Analysis: Self-Stigma
Self-stigma refers to the internalization of negative beliefs about mental health, leading individuals to view their own distress as weakness or failure (Thornicroft, et. al., 2022).
SPC Jones interprets his trauma responses as personal flaws rather than normal reactions to a disturbing event. These beliefs erode his confidence, contribute to anticipatory anxiety about his performance, and inhibit emotional connection with his partner.
Self-stigma is associated with reduced help-seeking, impaired self-esteem, and social withdrawal, all of which are visible in this interaction (Corrigan & Rao, 2012).
Act II: The Break Room
At work, Sean is distracted and struggling to get work done. His colleague Forsyth notices and asks him what’s going on. He opens up enough to admit he is having trouble sleeping. Forsyth suggests going to Behavioral Health, noting that the clinic really helped him manage his sleep issues and post-deployment stress.
Sean hesitates thinking, Forsyth deployed—his problems are "real." I’m messed up because of an accident that happened during training…and I wasn’t even the one in the accident! His own distress feels unjustified in comparison. Still, he makes a call to Behavioral Health during a break, hoping for an after-hours appointment that won’t interfere with duty hours.
No such luck—the only available times are during duty hours. As he’s on hold, his NCO walks by, loudly complaining:
“If one more soldier tells me they’re unavailable because of a ‘behavioral health appointment'— I'm going to go ballistic on them! These punks are a bunch of selfish wusses who don’t have what it takes to be real soldiers!”
Spotting Sean, the NCO comes over and claps him on the shoulder.
“But not SPC Jones here! Jones got what it takes and knows how to get the job done. He’s always mission-first!”
SPC Jones abruptly ends the call, discreetly putting his phone back in his pocket. He acknowledges his NCO and heads back to work without making an appointment.
Analysis: Public and Organizational Stigma
Public stigma involves negative stereotypes or prejudice from others—often peers, leaders, or society at large towards those with mental health conditions (Thornicroft, et. al., 2022). The NCO’s remarks reinforce the idea that seeking help is selfish or weak, which discourages soldiers from pursuing care—even when they need it.
Organizational stigma refers to structural barriers, such as limited availability of care during off-duty hours or command climates that discourage medical appointments (Thornicroft, et. al., 2022). In this case, both forms of stigma intersect to shut down Sean’s attempt to access care.
Act III: The Lunch Table
Meanwhile, Stacey meets friends for lunch. Tired from last night’s interrupted sleep, she yawns repeatedly. Her friends ask about it, and she hesitantly mentions Sean waking abruptly and shouting during the night.
One friend jokes: “you better watch out—make sure he doesn’t snap and kill you in your sleep!” The group laughs. Stacey forces a chuckle, then changes the subject. The comment unsettles her. She isn’t afraid of Sean, but she suddenly feels unsure about opening up to friends—or about asking him what's going on.
Analysis: Stigma by Association
Stigma by association occurs when family members or partners experience social rejection, judgment, or discomfort due to their relationship with someone perceived to have a mental health issue (Thornicroft, et. al., 2022).
Although the comment was meant as a joke, it reflects a damaging stereotype—linking mental illness to violence—and reinforces Stacey’s reluctance to seek support or ask questions. Like many military spouses, she may feel isolated from both her partner and her social circle.
Act IV: The Search
That evening, still troubled, Sean decides to look for a civilian provider outside the military system. He feels a glimmer of hope—maybe he can get help without his command knowing.
But the process is overwhelming. Who should he call—a counselor, psychologist, psychiatrist, psychiatric nurse practitioner? After a quick text exchange with Forsyth, he decides to call clinics that can prescribe medication. He finds one with availability—then he hears the cost: $300 for the intake, $150–$200 for follow-ups.
“Never mind,” he says, and ends the call. That faint hope disappears. He feels more lost than ever. Hopeless thoughts begin to surface. Maybe everyone would be better off without me, he thinks.
Analysis: Structural Stigma and Access Barriers
Sean’s final attempt highlights ongoing structural barriers to care outside the military: unclear provider roles, high out-of-pocket costs, and confusing systems of access.
Even when service members are motivated to seek care privately, these factors often lead to frustration, avoidance, and worsening distress (Kim et al., 2011). This moment illustrates how logistical obstacles can reinforce despair and delay treatment.
Conclusion: What Can Providers Do?
Understanding how stigma functions at every level—internal, interpersonal, and systemic—is key to helping service members like Sean. As providers, we can make a profound difference by intentionally addressing these barriers.
- As providers, we can: Normalize trauma responses during education and intake
- Address self-stigma explicitly in therapy
- Collaborate with commands to reduce public and organizational stigma
- Support spouses and families affected by stigma by association
- Advocate for accessible care pathways both within and outside the military system
By identifying and dismantling stigma—internally, interpersonally, and systemically—we can strengthen the mental health, relationships, and mission readiness of our service members (World Health Organization, 2024).
Resources
Military Crisis Line: Dial 988 and press 1, or visit VeteransCrisisLine.net
InTransition Program: https://www.health.mil/inTransition – Free, confidential coaching for service members transitioning between mental health providers
The opinions in CDP Staff Perspective blogs are solely those of the author and do not necessarily reflect the opinion of the Uniformed Services University of the Health Science or the Department of Defense.
Adria Williams, Ph.D., is a Military Behavioral Health Psychologist at the Center for Deployment Psychology (CDP) with the Uniformed Services University of the Health Sciences. Dr. Williams is a suicide prevention subject matter expert and trainer.
References
Corrigan, P.W. & Rao, D. (2012) On the self-stigma of mental illness: stages, disclosure, and
strategies for change. Canadian Journal of Psychiatry, 57(8):464–9
(https://doi.org/10.1177/070674371205700804).
Kim, P. Y., Britt, T. W., Klocko, R. P., Riviere, L. A., & Adler, A. B. (2011). Stigma, negative
attitudes about treatment, and utilization of mental health care among soldiers. Military
Psychology, 23(1), 65–81. (https://doi.org/10.1080/08995605.2011.534415).
Thornicroft G., Sunkel C., Aliev, A. A., Baker, S., Brohan, E., el Chammay, R., et al. (2022). The
Lancet Commission on Ending Stigma and Discrimination in Mental Health. Lancet,
400(10361):1438–80 (https://doi.org/10.1016/S0140-6736(22)01470-2).
World Health Organization (2024). Mosaic Toolkit to End Stigma and Discrimination in Mental
Health. Copenhagen: WHO Regional Office for Europe.
(https://www.who.int/europe/publications/i/item/9789289061384).
Staff Perspective: Language that Heals, Not Harms
July 23, 2025
 By
Behavioral health providers are crucial in combating the stigma that prevents service members from seeking mental health care. However, providers can inadvertently perpetuate this stigma through their language and tone. Phrases such as “depressed people,” “suffering from,” “mental illness,” or even casual remarks that minimize symptoms can alienate military clients who are already reluctant to engage. The most recent Department of Defense Health Related Behaviors Survey (2021) revealed that 1 in 4 active-duty personnel reported mental health concerns, yet fewer than half sought treatment, frequently citing fear of judgment. Providers, who adopt strength-based communication that recognizes the impact of individual differences, are vital in changing this dynamic and improving access to care.
Consider the perspective of a military member who silently experienced symptoms of PTSD for years. This individual avoided counseling, convinced it would damage their reputation and stall their military career. When a behavioral health provider embedded within their unit started using mission-ready terminology, framing mental health as “tactical readiness” and therapy as “resilience training,” the individual finally sought help. This not only alleviated their symptoms, but also enhanced their performance, prompting others in the unit to reflect on their own well-being. Such stories underscore that altering our approach to discussing mental health is not merely ethical, but also highly effective.
One tool that you can put in your toolbox to support this effort is the Mental Health Stigma Reduction Toolkit from the Psychological Health Center of Excellence (PHCoE). This comprehensive, evidence-based guide offers strategies for reducing stigma in various military settings. It provides templates, leadership messaging, and advice for refining clinical language to encourage engagement. Providers can actively dismantle barriers to care by integrating this toolkit and consistently using respectful, empowering language that highlights mission-readiness and resilience. In doing so, we not only support the individual but also bolster the strength of the entire force.
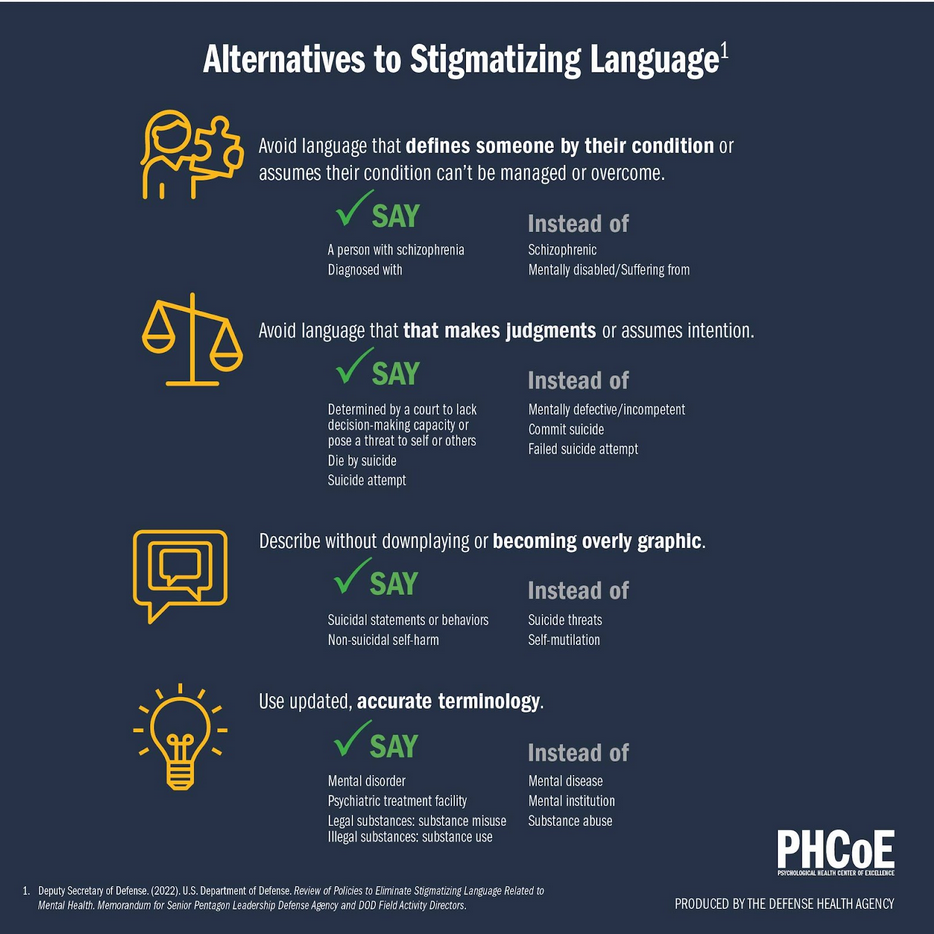
Source: Psychological Health Center for Excellence
The opinions in CDP Staff Perspective blogs are solely those of the author and do not necessarily reflect the opinion of the Uniformed Services University of the Health Science or the Department of Defense.
Annie Layden, LICSW, is a licensed clinical social worker working as a Military Behavioral Health Social Worker for the Center for Deployment Psychology at the Uniformed Services University of the Health Sciences in Bethesda, Maryland.
Staff Perspective: “Do you have children?” The Milspouse Elephant in the Room
July 16, 2025
 By Heather Tompkins, Ph.D, MS-ATR, LCMHC
Life as a military spouse is synonymous with frequent moves, starting over, and re-establishing connections. For a large portion of my married life, each PCS (Permanent Change of Station) and the initial social functions that followed brought with it a certain angst related to connecting- especially with other military spouses. Although I knew the intent was to meet, interact, and form connections, there tended to be an “elephant in the room” at each of these gatherings.
Do you have kids? An innocent question most spouses asked as an opener to start conversation. As newlyweds this question was easy to respond to. “No kids, but at some point.” Yet, as newlywed status fades and you have been married 3, 5, 10 years…this question starts to have a different impact- especially when “at some point” has not occurred.
While the military is comprised of ~1.31 million active-duty service members (MilitaryOneSource, 2023), within each of the service branches the subcommunities are not as large as you would think. Most specialty areas, such as aviators/pilots within the Marine Corps, either know each other or of each other from various interactions within their jobs. So, it is inevitable you will cross paths or be assigned to the same duty stations with the same people again. That is where the milspouse elephant in the room begins to become more blatant- it has been several years or duty stations since seeing this spouse and the looming question emerges, “do you have kids?” When the answer is “no” yet again, there exists this comfort to ask more… “do you want kids?” or “when are you going to have them?” For me, these interactions were typically followed by the formation of a knot in my stomach and deciding how to respond. Do I say what is really going through my mind or the practiced generic response. Unbeknownst to those asking, this internal dialogue was my source of angst during these social interactions- and I later learned was shared by others who experience infertility.
Within the general population, it is estimated that one in six people of reproductive age will experience infertility at some point (World Health Organization, 2024). Recent studies within the military community suggest those numbers may be higher. The Blue Star Families 2021 Military Lifestyle Survey found that 67% of respondents have experienced at least one family-building challenge, and the 2024 Military Family Building Survey from the Building Military Families Network found that 70% of respondents identified as having an infertility connection. The more I have learned and been open to talking about my own infertility journey, the more common I have found it to be within the military community.
Despite this occurrence, most military families experience various challenges to accessing fertility treatments. There are only six military treatment facilities (Fort Sam Brooke Army Medical Center, San Antonio, TX; Tripler Army Medical Center, Honolulu, HA; Walter Reed National Military Medical Center, Bethesda, MD; Womack Army Medical Center, Ft. Bragg, NC; Naval Medical Center, San Diego, CA; and Madigan Army Medical Center, Tacoma, WA) that offer Assisted Reproductive Technology (ART) at a reduced rate. For those referred to civilian providers the cost can double, even triple, with one round of In vitro fertilization (IVF) costing between $10,000-$25,000. Currently, Tricare policies only cover some of the expenses related to treating infertility. These consist of diagnostic services (i.e., semen analysis, hormone evaluation, chromosomal studies, immunologic studies, imaging studies, special and sperm function tests, bacteriologic investigation) and treatments to correct an underlying physical cause of infertility or erectile dysfunction stemming from a physical cause- all of which must be deemed medically necessary (Tricare, 2025). While working with a PCM and getting the necessary documentation in your medical record has its own set of challenges, once achieved, these foundational services at minimum provide military families a starting point to understanding their fertility and making an informed decision regarding treatment. While, TRICARE does not cover ART for common causes of infertility like polycystic ovary syndrome (PCOS), endometriosis, low sperm count or, in our case, unexplained infertility; it may cover ART, such as IUI and IVF, if the service member has suffered a documented service-related injury or illness causing their infertility. For service members, proof of service-connected infertility can pose additional challenges. Impacts to reproductive health and fertility is still being researched in terms of what may be causal factors (i.e., exposure to toxins, brain injury/combat injuries, medications, etc.,) and unless infertility is specifically identified through diagnostic testing or medical records, detecting the cause and providing service-connected proof remains a struggle.
In addition to diagnosis, insurance coverage/costs, and treatment, other challenges involve the cost and time to travel to/from multiple doctor appointments (and or military treatment facilitiy (MTF) depending on location), maneuvering schedules of both the spouse and service member, the cumulative costs for each appointment and cycle of treatment, storage fees for reproductive specimens, and access to medications (sometimes covered through MTF pharmacies depending on availability and location). While this may not sound different from a civilian couple seeking fertility treatment, these challenges are amplified when combined with normal military life that involves consistent separation, relocation, limited proximity to support systems, and routine changes to medical providers. The process becomes a revolving door of starting over resulting in delays for beginning a treatment, and ultimately a family. Over recent years, legislation has worked to increase coverage for infertility and ART benefits for military service members and their spouses. Although there have been some improvements, the resources and accessibility of these benefits remain limited, especially in comparison to some private insurance companies.
Navigating the logistics related to infertility treatment was its own set of challenges. What I was not prepared for was the emotional roller coaster that can come with this journey- much of which was experienced alone or only shared with those closest to me. As with all medicine, it is a practicing science, it can take several appointments and “cycles” to figure out what works for your body. This means getting your hopes up, then deflated when told the cycle was cancelled or unsuccessful, and then mentally preparing yourself to do it all again the following month or waiting “x” amount of time before starting again.
When looking at the statistics for successful ART (based on age, clinic, and treatment type) and talking with others who have experienced infertility, my spouse and I were relatively lucky. With our first child, we were able to complete treatment through an MTF. It took a year of diagnostic testing, work-ups, and specialist referrals, followed by four cancelled cycles and, on the fifth cycle and first IUI, success that gave us our son. A few years later, we were referred to a civilian provider for ART that consisted of six months of work-ups, one cancelled cycle, and success on our first IUI that gave us our daughter. Despite asking questions and reading, I felt ill prepared physically, mentally, and emotionally for everything this process entailed. Medical staff were always supportive; yet, in some ways, it was the re-emergence of the “elephant in the room;” an internal feeling of embarrassment, anxiety, and mixed emotions, surrounding the process. An experience I later found to be shared amongst others engaging in infertility treatment.
As I have found my voice and willingness to talk more openly about my infertility journey, I have found that the “elephant in the room” is no longer ignored and the resulting insecurities it caused resolved. I have a stronger sense of community with other spouses that have shared this journey, as well as feel confident that if my spouse and I choose to go through this process again, I am better prepared how to navigate and advocate for my family. In the meantime, my hope is that legislation continues to improve coverage for infertility and ART benefits to service members and their families. As for the milspouse elephant in the room question, “do you have kids”- I can now answer it with a smile and without angst, “Yes, I have two amazing kids” and am comfortable sharing my journey to be able to have them.
The opinions in CDP Staff Perspective blogs are solely those of the author and do not necessarily reflect the opinion of the Uniformed Services University of the Health Science or the Department of Defense.
Heather Tompkins, Ph.D, MS-ATR, LCMHC, is a Military Behavioral Health Psychologist with the Center for Deployment Psychology (CDP) at the Uniformed Services University of the Health Sciences in Bethesda, Maryland. In this role, she provides oversight and fosters collaboration for creative arts related research projects in partnership with the Defense Intrepid Network.
References
Building Military Families Network (2024). 2024 Military Family Building Survey.
https://static1.squarespace.com/static/64aae6434f45553f85234a2d/t/67fea5a58e10245
721eaafce/1744741797850/2024+Military+Family+Building+Survey+First+Look+%281%2
9.pdf
Blue Star Families (2021). Military Family Lifestyle Survey.
https://bluestarfam.org/wpcontent/uploads/2022/03/BSF_MFLS_Results2021_Compreh
ensiveReport_03_14.pdf
MilitaryOneSource. (2023). 2023 Demographics Profile of the Military Community (Department
of Defense).
https://download.militaryonesource.mil/12038/MOS/Reports/2023-demographics-repor
t.pdf
Tricare (2025). Covered Services: Infertility and Diagnosis and Treatment.
https://tricare.mil/coveredservices/isitcovered/infertilitytreatment.aspx
World Health Organization (WHO, 2024). Infertility.
https://www.who.int/news-room/fact-sheets/detail/infertility
Staff Perspective: Practice Makes … Improvement … If We Are Deliberate!
July 9, 2025
 By
Over the last year, I’ve been involved in a research project that looks at the effect of regular consultation on a therapists skill in delivering treatments like Cognitive Processing Therapy (CPT) and Cognitive Behavioral Therapy for Insomnia (CBT-I). Through the course of this project I’ve been thinking a lot about how we as therapists can improve in our craft over time. There is value in general experience, but experience alone is often insufficient to really improve.
Therapy is a unique activity. It is generally done in a highly private manner with little opportunity for feedback. In our graduate training we are observed and sometimes record sessions for review and feedback by our supervisors. Also, the level of direct observation and feedback is highly variable from one program to another, and once we graduate, this form of supervision generally ceases. Even if there is continued supervision it is often not direct observation with feedback, but a discussion of the patient with recommendations from the supervisor. However, over the course of our career, new treatments will be developed with new approaches and techniques. So how do we learn and master the skills and techniques associated with good therapy?
This is where I started to explore and learn about the concept of Deliberate Practice. Deliberate Practice is the intentional practice of specific skills, often with an expert or teachers help. It is repeated with feedback and can be a highly demanding mental activity. The concept has been made popular by the Malcolm Gladwell book Outliers. In the book, Gladwell refers to the research done by Anders Ericsson and colleague in 1993 “The Role of Deliberate Practice in the Acquisition of Expert Performance” and the “10,000 hour rule.” This rule suggests that 10,000 hours of practice in a discipline will produce expertise. However, this research is often misinterpreted and inappropriately applied. The key factor to consider is right in the name of the research article. Expertise is generally produced by high levels of deliberate practice.
So how do we engage in the act of deliberate practice in the field of psychotherapy? This is where the work of Tony Rousmaniere, Psy.D. has focused. Dr. Rousmaniere is the author of several books that focus of the topics of deliberate practice with psychotherapy and has founded Sentio University, which incorporates “skill-focused experiential Deliberate Practice training” as a central component of their educational model for an MFT program. The university also provides deliberate practice exercises that therapists can use to develop their own skill and competence in specific areas. They have developed practice exercises that focus on both general skills (validation, collaborative goal setting and providing a treatment rationale) to more model specific exercises (using CBT to work with problematic thoughts). The goal of this is to break down what we are doing into discrete components and then practice … deliberately.
Providing trauma therapy can be challenging and daunting for therapists. It requires the therapist to have a strong understanding of the theoretical framework of the treatment protocol, mastery of the foundational skills associated with the treatment and comfort working with the trauma content. But, if we start to think about the discrete components of the treatment and engage in deliberate practice, this can all become more manageable. We can start by breaking things down, first in the more general. For example, “How to explain what PTSD is”, “Answering common questions that patients have about PTSD” and “How to explain treatment options and the rationale for those treatments.” You can start by simply recording yourself, listen to it, do it again. Make sure that you are accurately describing the theory. You can chose to engage the feedback of a trusted colleague or expert in the field. From there you can apply the same process to different treatment modalities. If we take CPT as an example, start with explaining cognitive theory and answering common questions, record and repeat. Apply this to introducing stuck points, ABC worksheets, etc. Take it one step at a time, evaluate yourself, get feedback from others.
Being a therapist is a lifelong journey of learning where graduate school is just the beginning of that journey. Participating in the trainings that we provide is a fantastic step in gaining greater knowledge, but to become an expert… it takes deliberate practice. Give it a shot and let us know how we can help in your journey!
The opinions in CDP Staff Perspective blogs are solely those of the author and do not necessarily reflect the opinion of the Uniformed Services University of the Health Science or the Department of Defense.
Jeff Mann, Psy.D. is a Military Behavioral Health Psychologist at the Center for Deployment Psychology (CDP) at the Uniformed Services University of the Health Sciences (USU) in Bethesda, Maryland.